Hamstring injuries are a frequent hurdle in professional football, often sidelining players for weeks or even months. Among these, tendon or aponeurosis injuries—especially the intramuscular tendon (IMT)—are notorious for prolonged healing times and high recurrence risks due to the tendon’s role in force transmission during explosive movements like sprinting and shooting [1,2].
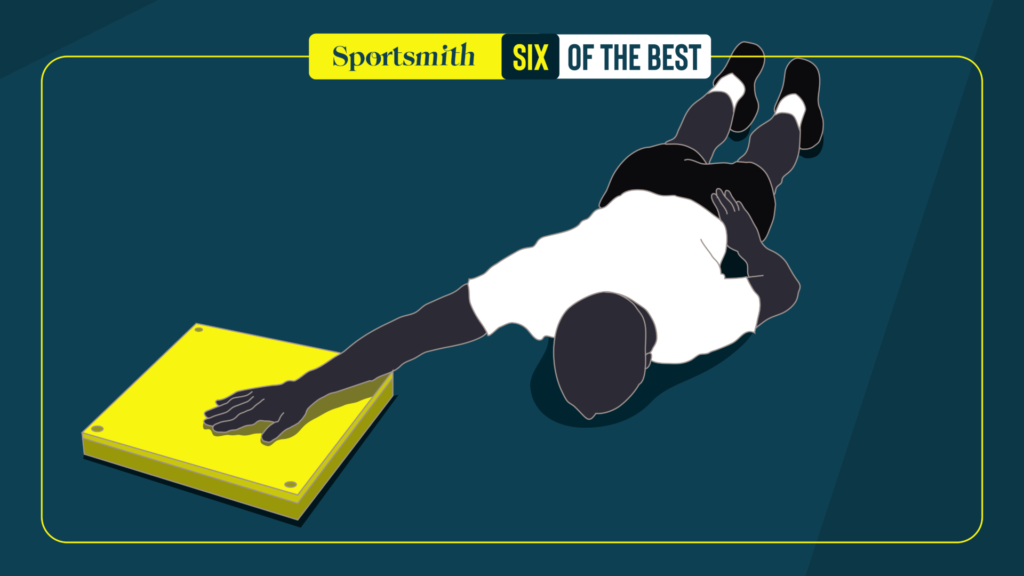
This case study dives into a professional footballer’s rehab from a BAMIC grade 2c longitudinal split of the conjoint tendon of the biceps femoris long head (Figure 1).
It outlines the player’s evidence-based rehab journey, integrating advanced monitoring tools—including thermography—and an innovative rehab performance framework to safely return him to play in four weeks.

Tweet ThisTendon or aponeurosis hamstring injuries, especially the intramuscular tendon, are notorious for prolonged healing times and high recurrence risks due to the tendon’s role in explosive movements like sprinting and shooting
@prller
Injury mechanism, diagnosis, and initial assessment
A 31 year old professional striker sustained a grade 2c longitudinal tear of the intramuscular conjoint tendon in the biceps femoris long head during a high speed defensive pressing action. The injury mechanism involved a direct contact collision while lunging forward with the trunk flexed and knee extended, placing extreme eccentric load on the hamstring at a lengthened position. He rated his pain as 6/10, and pain was localized to 10 cm x 3 cm on the proximal posterior thigh.
Under the British Athletics muscle injury classification (BAMIC) scale [3], this injury’s “2c” designation highlights moderate severity with critical intramuscular tendon involvement.
Intramuscular tendon injuries (BAMIC “c”) are associated with prolonged recovery, averaging 36 days, compared to 24 days for non-tendon injuries; and a higher reinjury rate—up to 63% in some cohorts [4]. The risk of reinjury rises if the athlete returns to play prematurely, emphasizing the need for a tailored rehabilitation approach.
MRI played a pivotal role in the first 72 hours for an early and accurate diagnosis, confirming tendon involvement.
The most important aspect to take into account is the exact location and the amount of connective tissue affected. Unlike superficial muscle strains, intramuscular tendon injuries are challenging to assess with standard imaging (i.e., ultrasound), underscoring MRI’s importance in prognosis and monitoring [5].
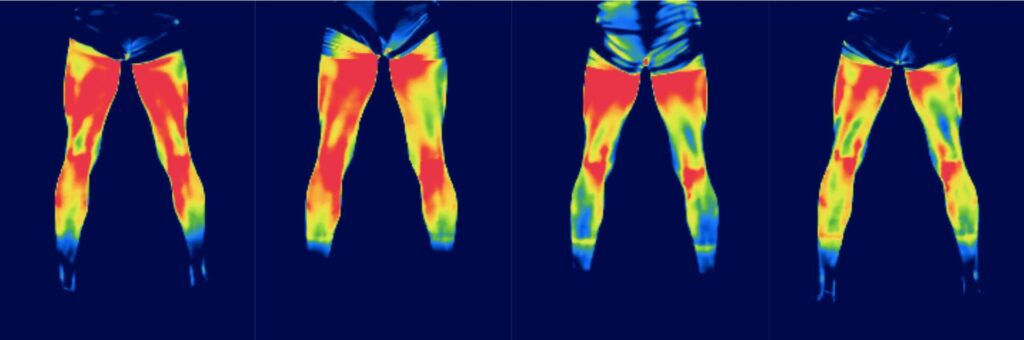
Thermography is a non-invasive imaging technique that detects infrared radiation emitted from the body to create a thermal map. In conjunction with traditional test methods such as force plates, handheld dynanometers, and GPS, practitioners and medical staff can use thermography to quantify internal response to an external load.
This player had his first thermography scan three days post-injury (Figures 2 and 3) to provide an objective starting point for how the injury would evolve thermally over time.
A hypothermic deviation (-0.82°C, in this case) marks the first 2-3 days after an injury, and harmonises slowly with recovery. Three factors underlie this hypothermic response: a lack of muscle contraction, a potential small static bleed, and a nervous system reaction.
This delta persisted during the first month (-0.30°C). The gradual return to equal temperatures on the injured and non-injured limb helps us quantify the player’s recovery and readiness between each training session; and, along with other KPIs, helps us make better decisions about daily training and return to play decisions.


Tweet ThisA hypothermic deviation (-0.82°C, in this case) marks the first 2-3 days after an injury, and harmonises slowly with recovery. Three factors underlie this hypothermic response: a lack of muscle contraction, a potential small static bleed, and a nervous system reaction
@prller
Challenges of intramuscular tendon injuries
Injuries to the biceps femoris free tendon and the common tendon have the worst prognoses. This player’s intramuscular tendon (IMT) or aponeurosis injury of the common tendon takes longer to heal (normally 2-3 times longer) than “simple” myofascial or musculotendinous injuries, and may have a higher risk of re-injury.
Pushing too hard, too soon, can reverse progress and cause a setback or even a larger injury [3,4,9].
However, this player’s MRI revealed a longitudinal split of the conjoint tendon. These have a more “favorable” prognosis, in that they are not associated with an increased risk of reinjury [10].
Return to play decisions require a strategic assessment of risk and risk tolerance (STARRt) [11]. Given the full context of the team, there was an urge to push the envelope and take the risk for a four-week return to play process. Because of the more favorable MRI signs, the player’s willingness, and supportive club culture, the multidisciplinary team, technical staff, and player agreed on this more aggressive RTP approach.

Principles for rehab phases
The rehab framework blended several evidence based principles to balance tissue healing, functional restoration, and psychological readiness.
Protect and prime (Days 0-3)
The acute phase emphasises tendon protection by completely avoiding tensile loading that would result in hamstring lengthening / shortening. We did not program stretching nor isometrics in the first phase.
This protection phase is a great opportunity to begin education, set goals, and discuss the rehab road ahead with the athlete. It is critical to target the contributing factors and any deficient areas that we identified in his pre-season or daily MSK screening.
From day one, we addressed his limited hip and thoracolumbar mobility (Videos 1-5), lateral hip strength, lumbopelvic control—particularly managing his anterior pelvic tilt in mid stance—arthrogenic muscle inhibition, and neurodynamics [15].
Initial modalities include manual therapy, neural mobilization, neuromusclar electrical stimulation with blood flow restriction, percutaneous needle electrolysis, thermal, passive / active mobilization, and accessory and hip lock exercises.
Hip and spine mobilisation drills
Restore and rebuild (Days 4-10)
This stage started with low jerk, 10-30 second isometric holds (more knee dominant than hip dominant) to promote collagen proliferation and reorganization without overloading the tendon. Blood flow restriction training is a great tool for imposing training stress without overloading the tendon. Low load BFR can improve Achilles and patellar tendon mechanical and morphological properties to a similar extent as conventional high load resistance training [16, 17].
The player gradually progressed to long length and more hip dominant positions. Submaximal eccentrics, such as slider leg curls or manual resistance, were introduced apart from intersegmental control / strength exercises such as step up, single leg RDL, and lunge.
He passed the return to running criteria by day 8 by ticking the following boxes. First, tenderness at the region of interest decreased from 10 cm to 3 cm. Thermography showed improved thermal evolution (-0.74 °C). He could perform single leg submaximal eccentric sliders, low amplitude running drills (ankle dribbles) and low intensity plyos (pogos); achieved 1.5-2x body weight in a run-specific hip iso push; and had symmetrical pain free hamstring mobility.
Before entering the on-field rehab phase on day 10, we started in the gym with two treadmill runs of 2-3 minutes intervals at 10-12 km/hr (Table 1, Videos 6-15).

Tweet ThisDays 4-10 started with low jerk, 10-30 second isometric holds (more knee dominant than hip dominant) to promote collagen proliferation and reorganization without overloading the tendon. BFR training is a great tool for imposing training stress without overloading
@prller
Restore and rebuild exercises: Intersegmental strength / control, isometrics, running ABC drills


Video 7. Barbell step


Functional on-field rehab (Days 11-21)
Working with the fitness coach, we planned the on-field rehab phase based on the control to chaos continuum [18].
The first microcycle (days 11-16) of on-field training followed an alternating load / rest (i.e., on-off) strategy to allow tissue recovery and adaptation. A “fast to fit approach” rebuilt the player’s load capacity. Due to the high risk of setback or re-injury of the connective tissue, we limited the maximum speed to 65% (~21-22 km/h) of his maximal sprint speed of 32 km/h.
The second microcycle aimed for single game load volumes of high speed running; half game load for very high speed running; and 1.5-2x game load for total distance and explosive distance. Based on his MRI from day 16, we felt more comfortable reaching 80-90% (28-29km/h) MSS by the end of this cycle.
While we progressed to a two day training block (on-on-off) for on-field rehab, we microdosed his gym work rather than programming one big gym session.
Based on whether the on-field rehab was going to be intensive or extensive, we tailored the activation to address his need for tendon robustness and deficits. We introduced exercises to prepare him mentally and physically to re-create and re-experience the mechanism of injury. Reflexive eccentrics, long length rapid eccentric decelerations (chop curl exercise stream), and decelerations with hip flexion, knee extension, and trunk perturbations (rotation, lateral flexion) were integral parts of the activation exercises.
The vertical and horizontal sprint mechanics drills played an important role in the rehab for an efficient movement pattern to reduce the stress on the connective tissue (Table 2, Videos 16-25).
Tweet ThisWorking with the fitness coach, we planned the on-field rehab phase based on the control to chaos continuum. A “fast to fit” approach rebuilt the player’s load capacity.
@prller
Videos 16-25. Functional rehab exercises: Intersegmental strength / control, isometrics, reflexive eccentrics, running mechanics vertical and horizontal drills.
By the end of this stage, the player was back at pre-injury strength levels for Nordics (eccentric hamstring), 90-90 Askling tests, and hip isometric rate of force development.
Return to team training (Weeks 3-4)
By the end of week 3, the player was ready to participate in team training. During this week, load management was key to not overloading or underloading him in preparation for the upcoming weekend game. We scheduled another MRI to evaluate the progress of the tendon healing by day 25 (MD-3). The MRI revealed scar maturation with little edema, an MRI milestone during the healing process of a connective tissue injury. That supported our goal of returning him to play that weekend with a decreased risk of reinury.
In addition to meeting the MRI based milestone, the patient demonstrated exceptional functional progress, achieving >95% maximal strength symmetry during the MD-2 assessment.
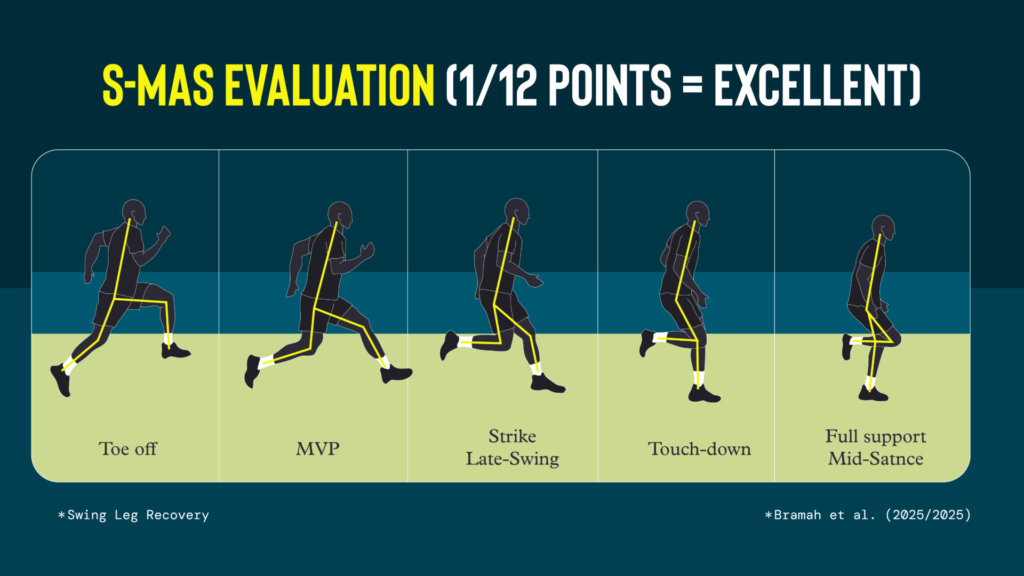
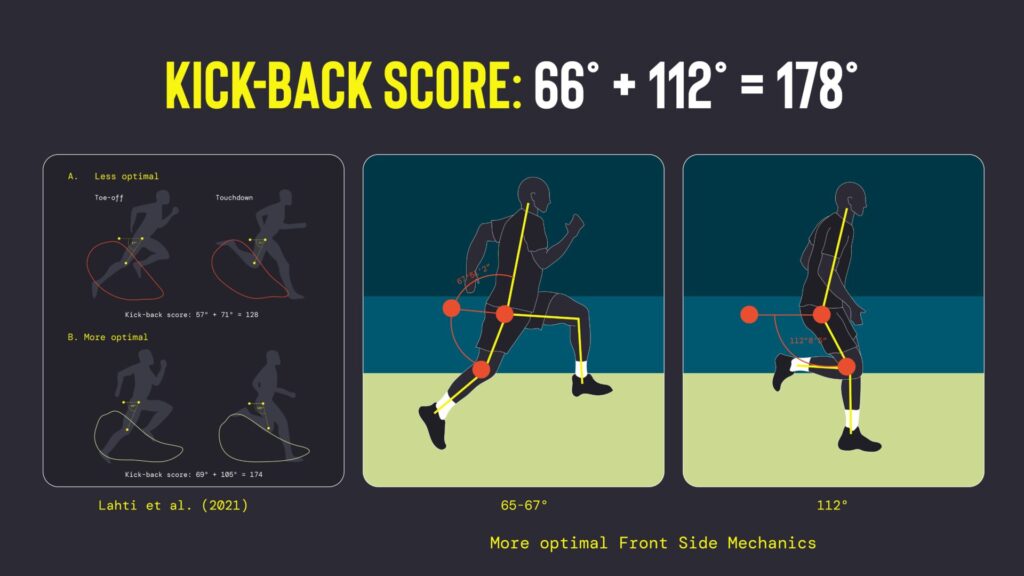
The kickback score [12] and Sprint Mechanics Assessment Score (S-MAS) [19] corroborated this progress, with an exemplary technical proficiency score of 1/12 (Figures 7-8).
He satisfied all criteria for return to play clearance with the exception of sufficient time to ensure complete connective tissue healing. Clinically, he had no tenderness, full range of motion, and performed the Askling test without apprehension. He was meeting game load demands and produced greater than 90% strength symmetry. His movement mechanics were excellent; MRI showed continued tendon healing; and themography confirmed progress towards a symmetrical thermal profiles. Finally, he was mentally ready, letting us know that he was keen to play 75 minutes in a game.
Return to play and performance (Day 28+)
The player returned to full team training at week 3 and competitive play by week 4. He successfully played 77 minutes in his first match post-injury, with no medical issues.
GPS data revealed a performance gap: his sprint distance and maximum sprint speed lagged behind pre-injury averages (Table 4). This aligns with a study suggesting lingering neuromuscular inhibition or psychological hesitancy post-recovery [20].
Following return to play, the athlete faced a congested schedule with a truncated three day recovery period, necessitating prioritized load management.
To evaluate his internal response to the match, we conducted an isometric hamstring test (isometric 90-90 on a Force Frame) and thermography on MD-2.
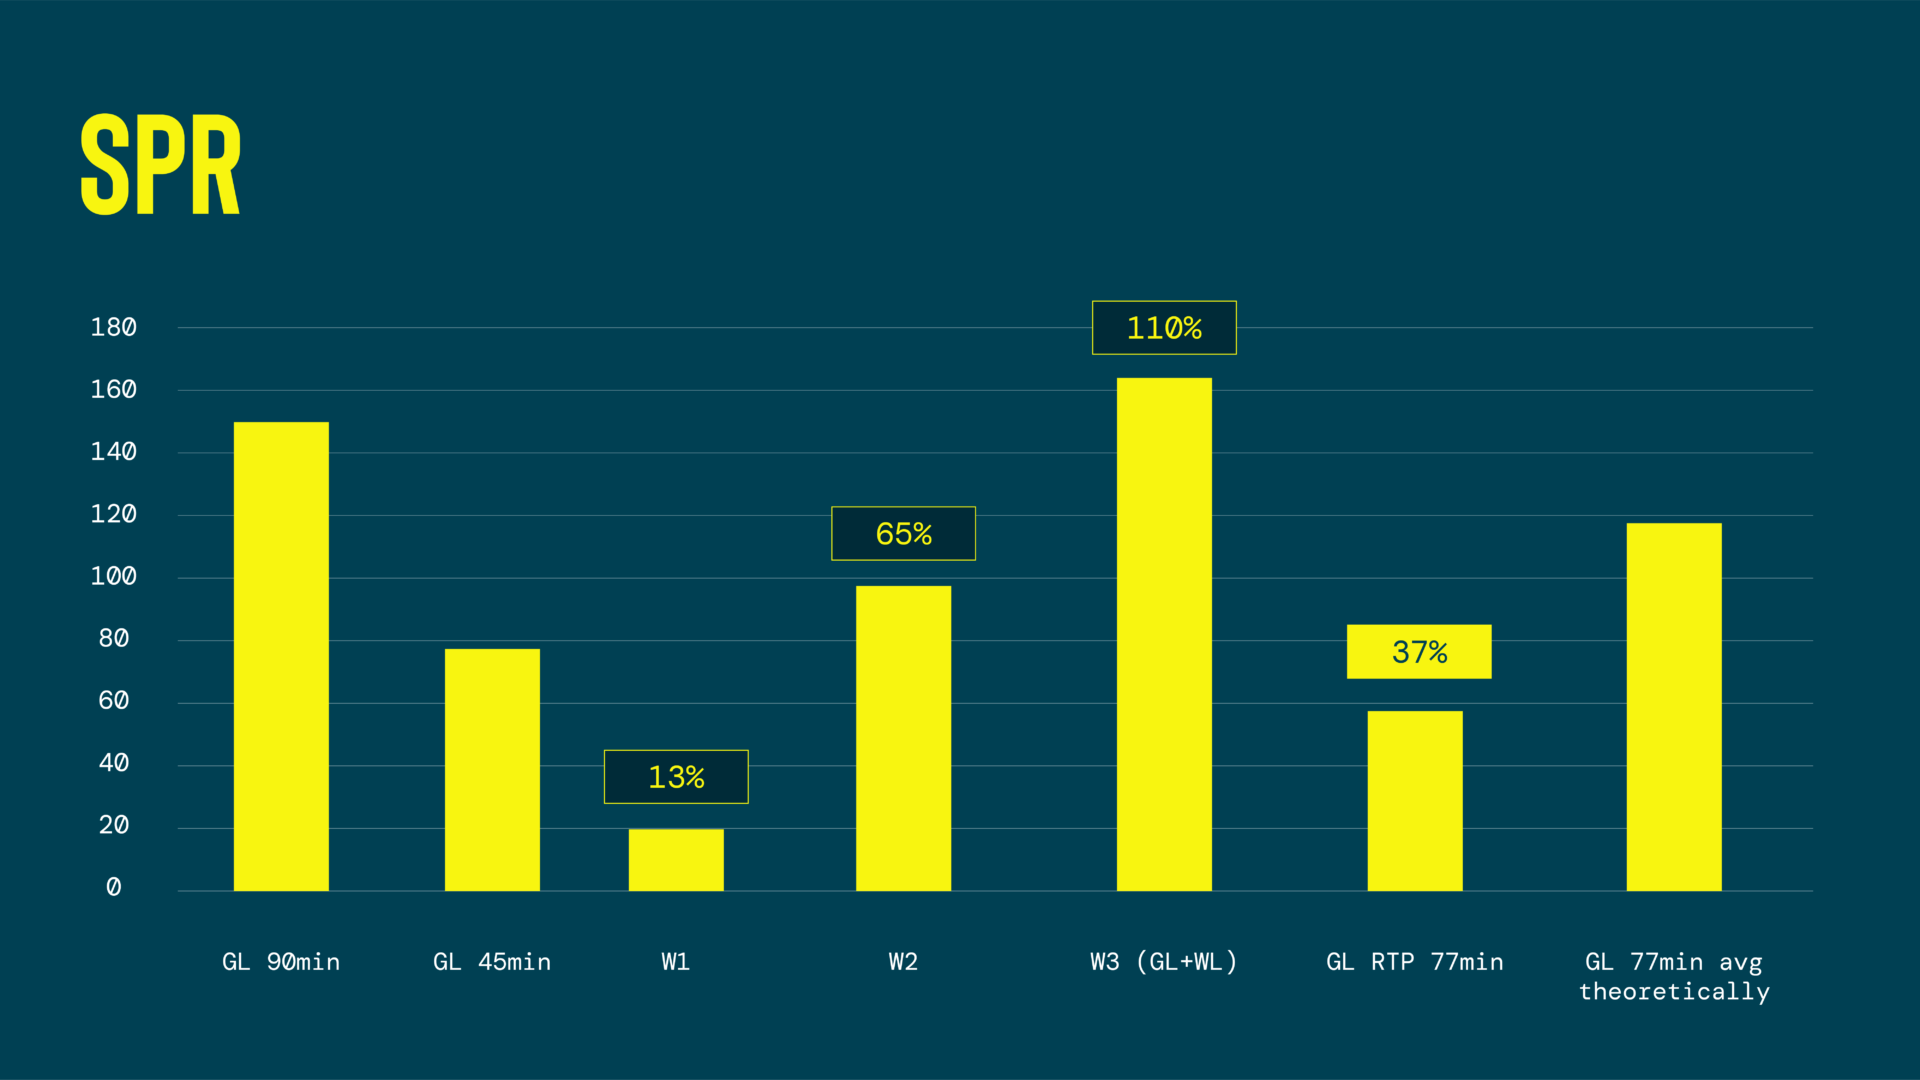
Given the congested schedule, we initially planned for him to play a conservative 50-60 minutes to balance competitive demands with physiological recovery. Tactical constraints during the match precluded substitution opportunities, resulting in him playing 85 minutes. Post-match GPS analysis revealed marked improvements in performance metrics from his first game back, including maximum sprint speed, sprint dstance, and total distance, indicating enhanced functional capacity and readiness under competitive load without any medical issues (Table 4, Figure 6).
Tweet ThisGPS data revealed a performance gap: his sprint distance and maximum sprint speed lagged behind pre-injury averages. This aligns with a study suggesting lingering neuromuscular inhibition or psychological hesitancy post-recovery
@prller

| Player Load 10.03.2025 – 30.03.2025 | |||||
| TD | HSR | SPR | ACC | MSS | |
| GL 90min | 10200 | 650 | 150 | 45 | 32.2 |
| GL 45min | 5100 | 325 | 75 | 23 | 32.2 |
| W1 | 12760 | 325 | 20 | 10 | 20 |
| W2 | 24588 | 781 | 98 | 89 | 28.3 |
| W3 (GL+WL) | 26529 | 1242 | 165 | 106 | 30.6 |
| GL RTP 77min | 8200 | 500 | 56 | 34 | 26 |
| GL 77min avg theoretically | 7854 | 501 | 116 | 35 | – |
| W1 % GL | 125 | 50 | 13 | 22 | 62.1 |
| W2 % GL | 241 | 120 | 65 | 198 | 87.9 |
| W3 % GL | 260 | 191 | 110 | 236 | 95 |
| GLRTP77min % GL | 80 | 77 | 37 | 76 | 81 |
This case highlights the importance of a multidisciplinary, data informed, risk based approach to decision making for an intramuscular tendon hamstring injury. By integrating imaging, objective data, and strategic assessments of risk and risk tolerance, we were able to successfully rehab this athlete earlier than expected in terms of biological healing time.
Injury rehabilitation is as much an art as it is a science. Knowing when to push and when to pause defines success.
Tweet ThisBy integrating imaging, objective data, and strategic assessments of risk and risk tolerance, we were able to successfully rehab this athlete earlier than expected in terms of biological healing time.
@prller
This article is supported by ThermoHuman